

Keypoints
What is known
– Channelopathies, such as KCNQ2-related disorders, are a genetic cause of neonatal seizures.
– Genetic testing allows for etiological diagnosis, which has crucial implications for therapy.
– These conditions respond well to sodium channel blockers, such as phenytoin and carbamazepine.
What is added
– Historically, KNCQ2-related disorders were divided into self-limited neonatal epilepsy and neonatal epileptic encephalopathy. However, it is now known they have a spectrum of presentations, as we present in this article.
– Our cases also reflect the absence of a linear correlation between genotype and phenotype.
Introduction
KCNQ2-related disorders are channelopathies caused by pathogenic variants in the potassium channel subunit gene, KCNQ2. The clinical presentation is characterized by neonatal-onset seizures, with a wide phenotypic spectrum ranging from self-limited neonatal epilepsy (SNE) to neonatal epileptic encephalopathy (NEE). SNE is associated with a favorable prognosis, including seizure resolution within the first 6-12 months of life and normal neurodevelopment. In contrast, NEE is characterized by more refractory seizures, which may nonetheless improve during early childhood, and is typically associated with moderate to severe neurodevelopmental delay.1,2
In a pediatric neurology outpatient setting at a level II hospital, three patients were identified who exemplified the clinical variability of KCNQ2-related disorders.
Case reports
Case 1: a male infant was born at term following an uneventful pregnancy, with normal fetal ultrasounds and maternal serologic testing. The infant was delivered at 40 weeks’ gestation, with Apgar scores of 9/10, and a birth weight appropriate for gestational age. During the second half of pregnancy and until delivery, the mother had been treated with 100 mg/day of sertraline and 1 mg/day of lorazepam. There was no family history of epilepsy, neurological conditions, or developmental disorders. The infant was discharged clinically well at 48 hours of life.
On day 3 of life, however, he developed brief episodes characterized by impaired awareness, ocular deviation, bilateral hypertonia, clonic movements beginning in the right upper limb with secondary generalization, facial flushing, and central cyanosis. An interictal examination revealed axial hypotonia. Initial electroencephalography (EEG) demonstrated bilateral paroxysmal epileptiform activity (Fig. 1A). The seizures were controlled with phenobarbital, which was discontinued at 4 months of age. Follow-up EEGs after treatment initiation (Fig. 1B), metabolic evaluation, transfontanellar ultrasound, and brain magnetic resonance imaging (MRI) were normal.
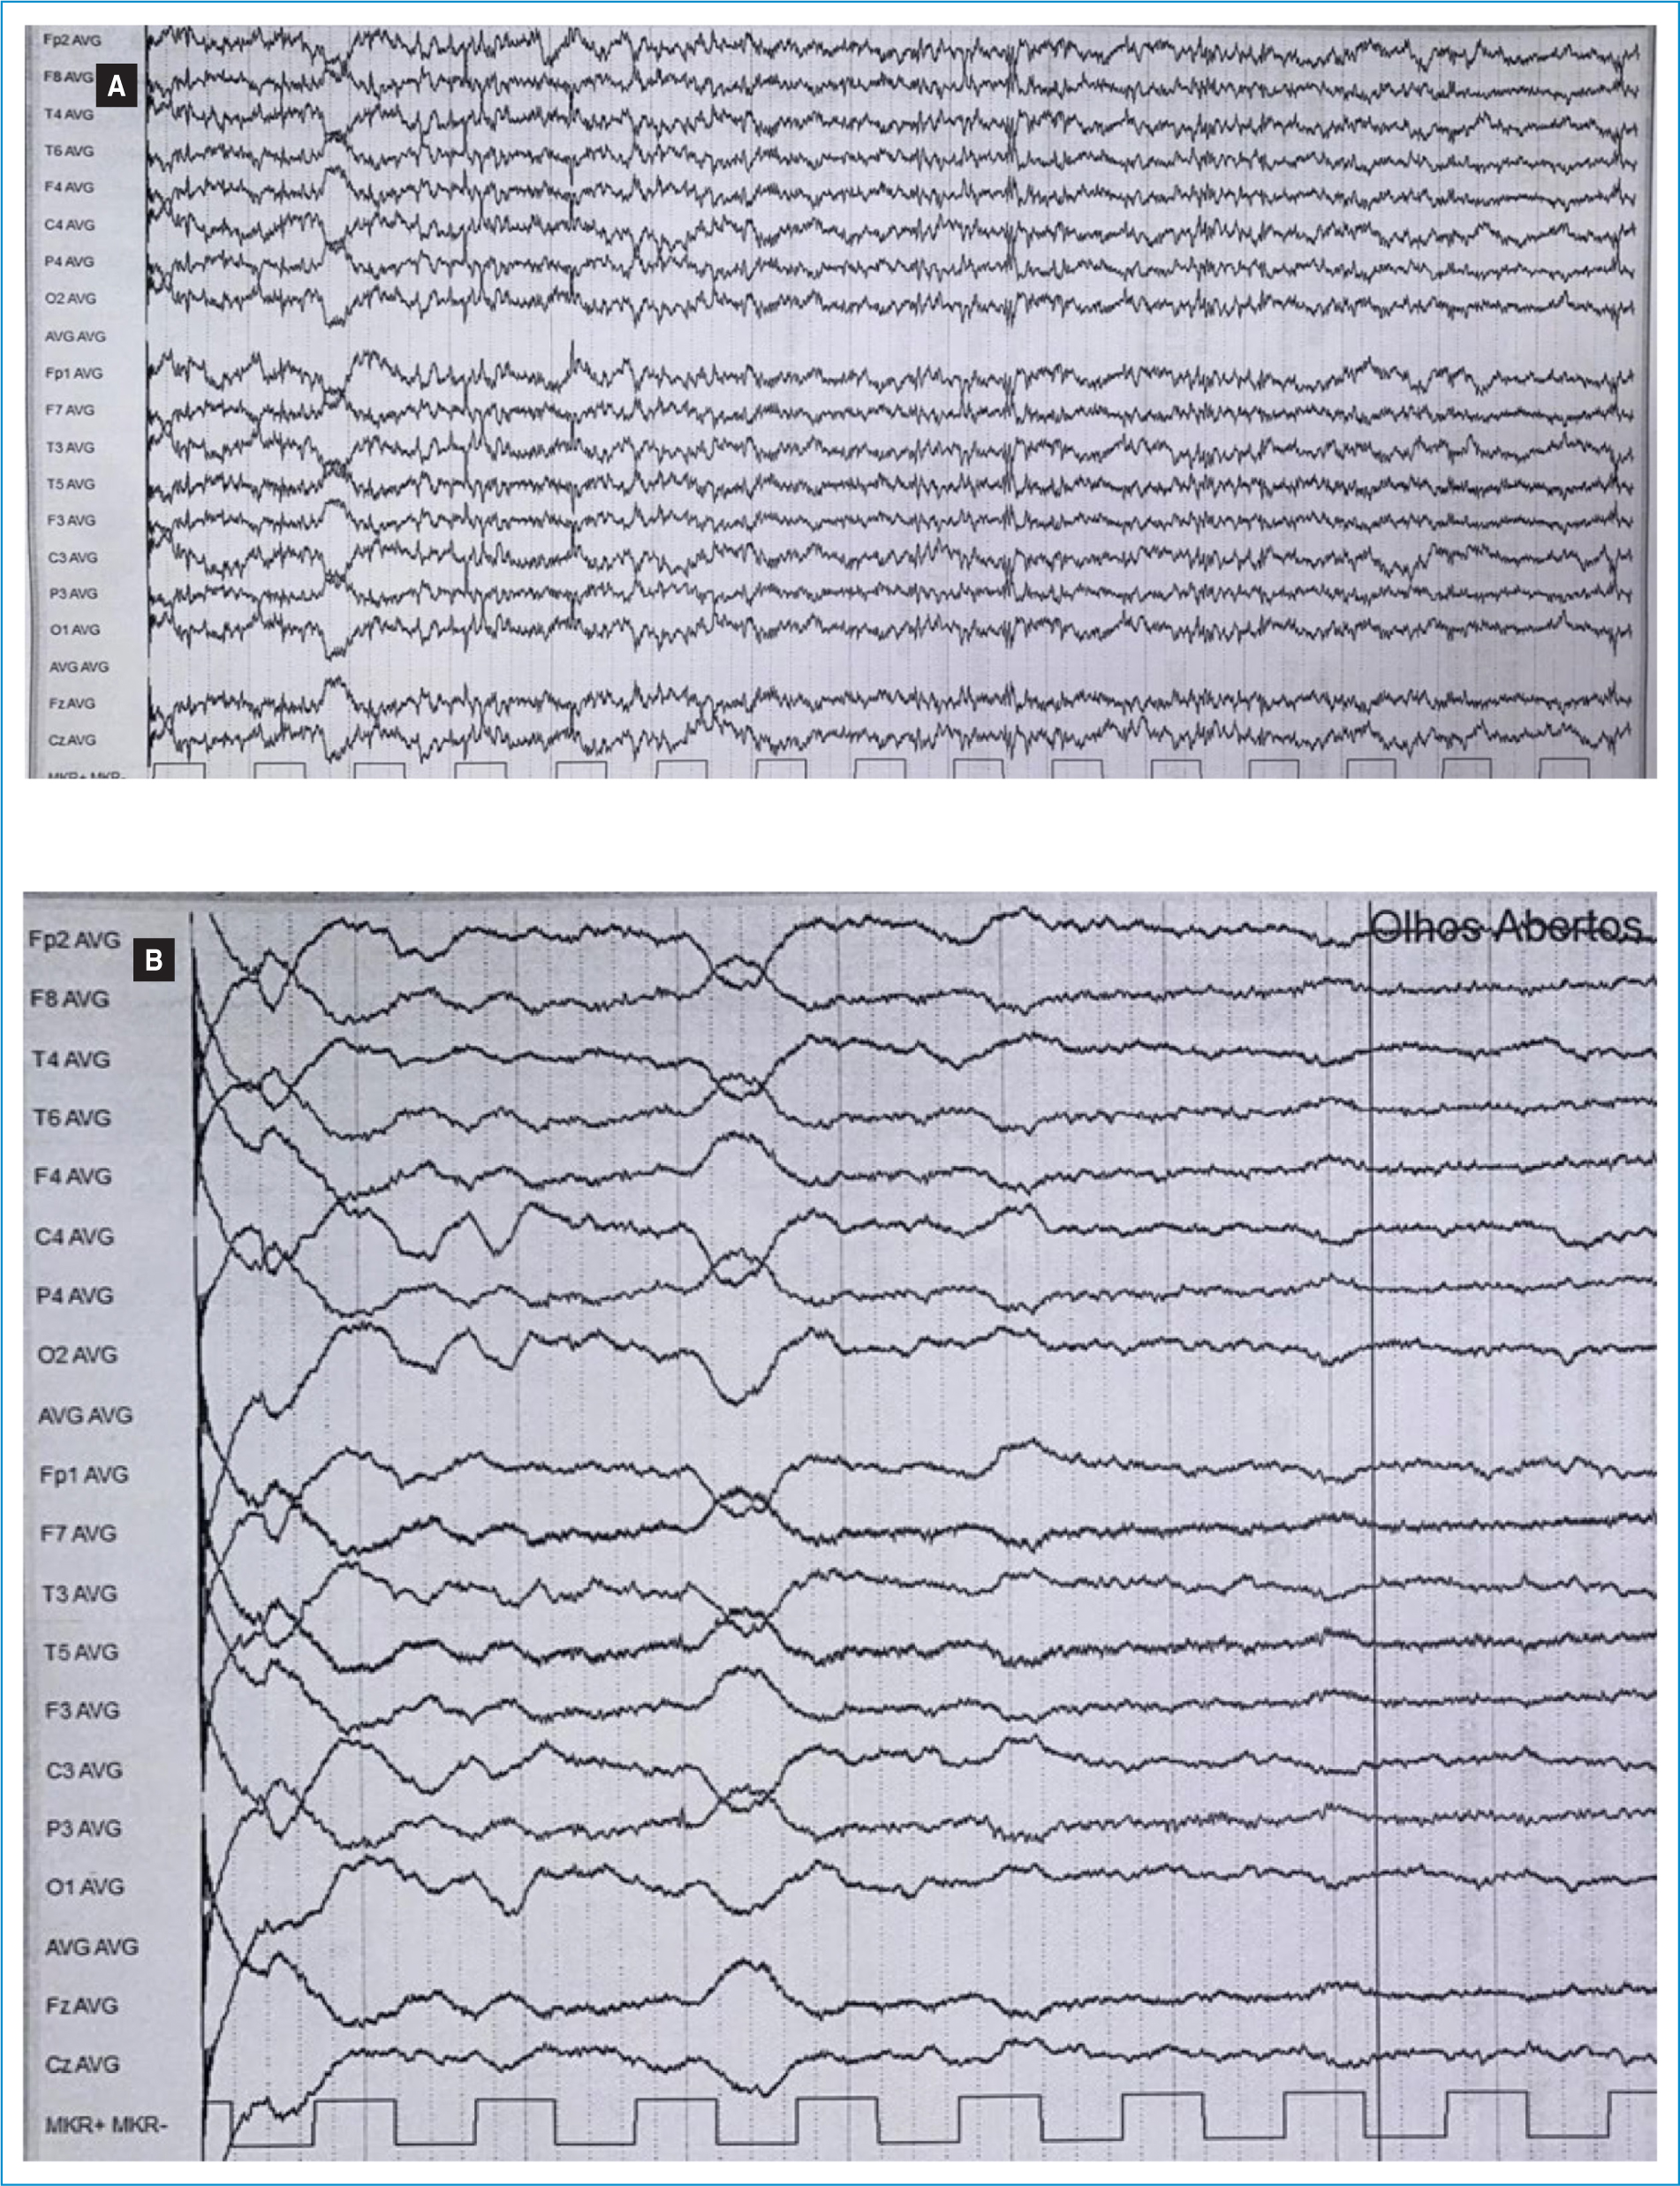
Figure 1. EEG findings. A: EEG on admission (bilateral activity). B: EEG after treatment (normal).
A next-generation sequencing (NGS) epilepsy panel (version 8, 230 genes) identified a heterozygous deletion involving exon 15 and flanking intronic regions of the KCNQ2 [NM_172107.3:c.(1631+1_1632−1)(1763+1_1764−1)del]. This variant had not been previously described and was initially classified as a variant of uncertain significance.3 The same variant was identified in one parent, suggesting either undetected neonatal seizures or incomplete penetrance, and was subsequently reclassified as likely pathogenic. At 30 months of age, the child remains seizure-free and has normal neurodevelopment.
Cases 2 and 3: female twins were born from a dichorionic, diamniotic twin pregnancy complicated only by late prematurity. Fetal ultrasounds, fetal echocardiograms, and maternal serologic testing were unremarkable. The delivery was by elective cesarean section at 36 weeks. Both infants had one-minute Apgar scores of 9 and five-minute Apgar scores of 10. They were appropriate for gestational age and discharged on day 2 of life. The family history was notable due to a 13-year-old brother with autism spectrum disorder and a maternal uncle with epilepsy.
Twin 1: on day 2 of life, the first twin developed seizure episodes characterized by cyanosis, left oculocephalic deviation, and tonic posturing of the upper limbs toward the left. An interictal examination revealed axial hypotonia and limb hypertonia. The initial EEG demonstrated multifocal epileptiform activity (Fig. 2). Seizures were initially controlled with phenobarbital. At 3 months and 3 weeks of age, seizures recurred, prompting the initiation of vigabatrin treatment. At 4 months, further seizure worsening led to the addition of levetiracetam without clinical response, followed by status epilepticus, which responded promptly to phenytoin.
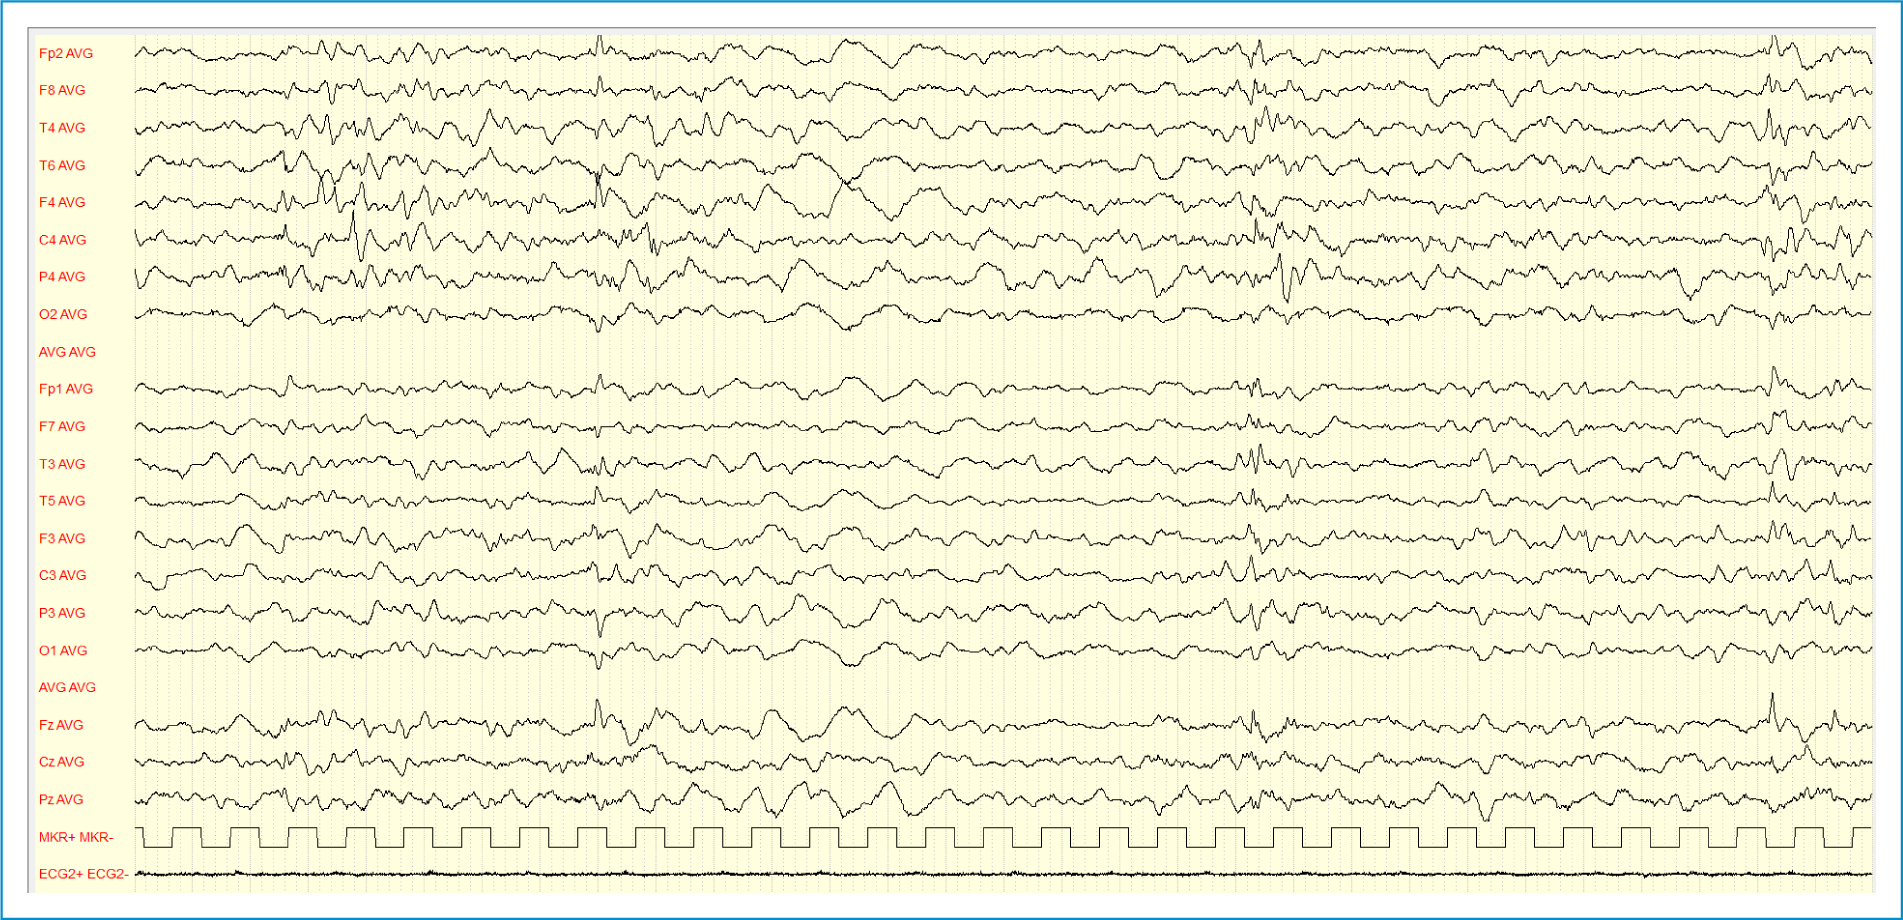
Figure 2. EEG on admission (right temporal and frontal activity).
Twin 2: on day 3 of life, the second twin developed seizures, characterized by tonic limb posturing, rightward ocular deviation, and clonic movements of the right hemibody. The seizures were initially controlled with phenobarbital. An interictal examination revealed limb hypertonia, and an EEG demonstrated multifocal epileptiform activity (Fig. 3). Due to seizure recurrence at 4 months of age, levetiracetam was initiated, without response. Like her sister, she developed status epilepticus that responded well to phenytoin.
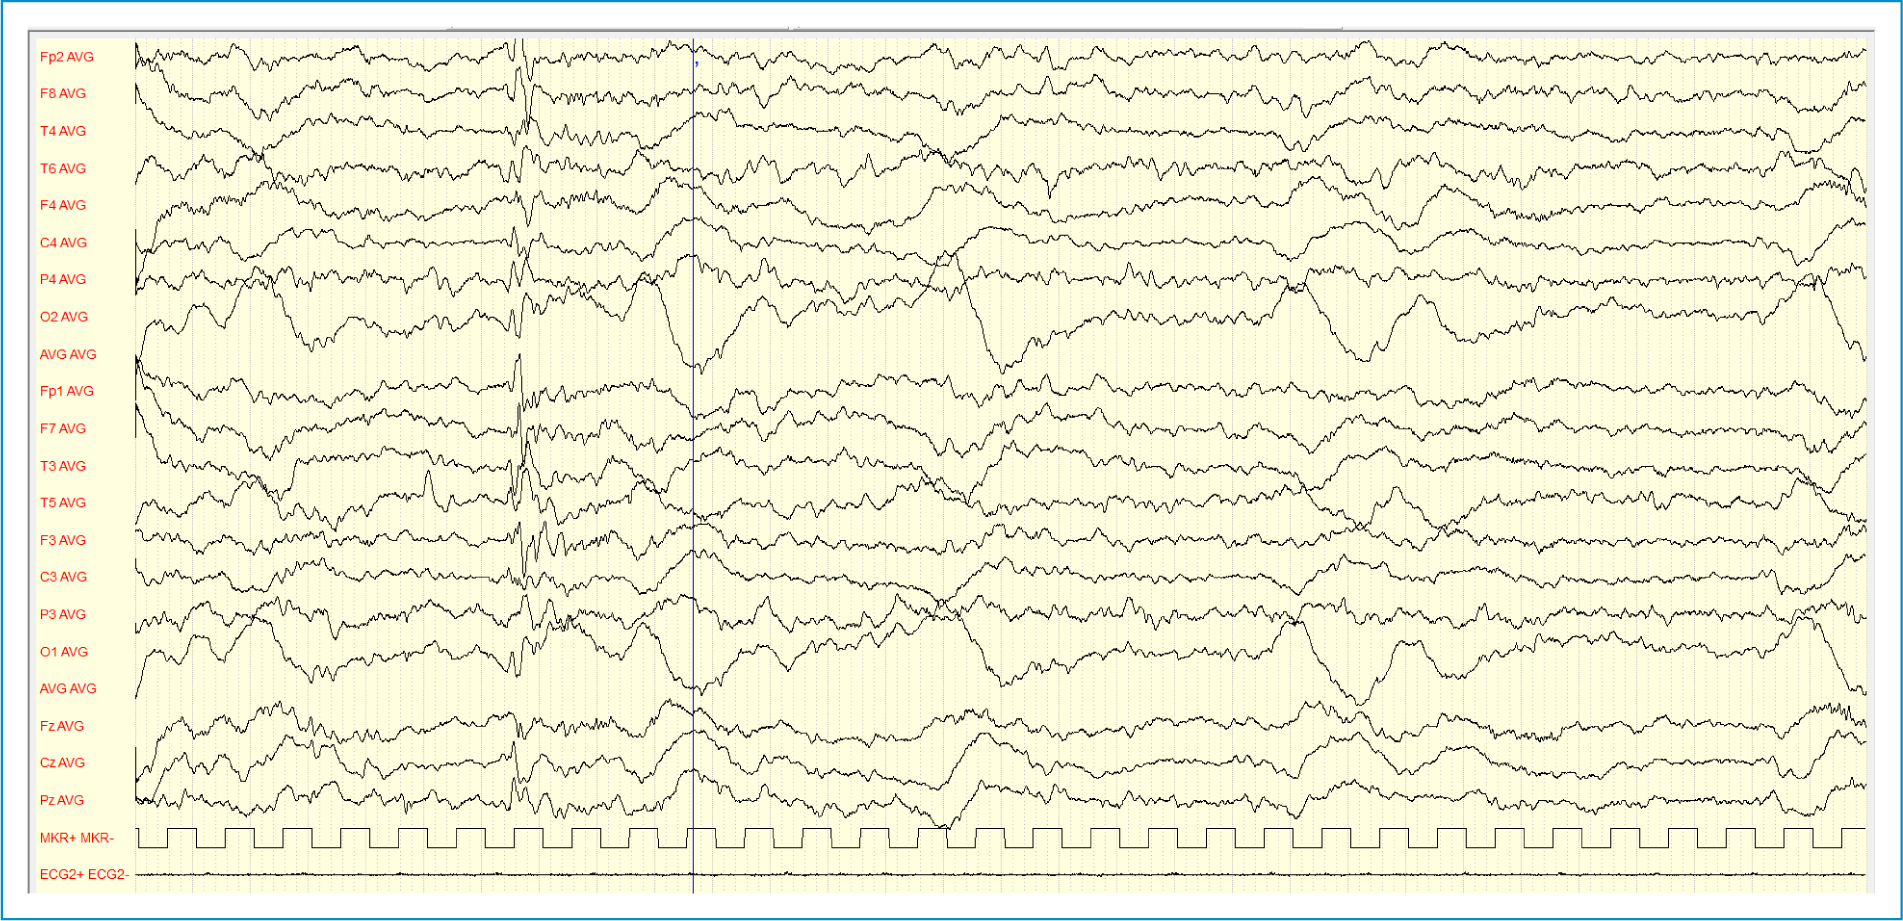
Figure 3. EEG on admission (bilateral temporal and frontal activity).
Both twins had normal metabolic studies and normal brain MRI findings. An NGS epilepsy panel (version 9, 266 genes) identified a previously undescribed heterozygous missense variant in both patients: KCNQ2 NM_172107.3:c.685A>G (p.Tyr562Cys). This variant was initially classified as having uncertain significance. Parental testing did not identify the variant, indicating a de novo mutation. Further genetic analysis, including bioinformatic assessment and confirmation of monozygosity, reclassified the variant as likely pathogenic.3
Following the genetic diagnosis, carbamazepine treatment was initiated, and phenytoin was gradually discontinued. Vigabatrin and levetiracetam were successfully withdrawn from the first twin by 28 months of age. Both patients have remained on carbamazepine since 10 months of age.
The first twin remained seizure-free from 5 to 15 months of age, after which she experienced two brief episodes of impaired awareness without identifiable triggers. She has been seizure-free since then while on carbamazepine (6 mg/kg/day). At 3 years and 4 months of age, she exhibits mild neurodevelopmental delay, particularly in language and sensory processing, with a normal neurological examination. Serial EEGs at 5, 9, and 16 months showed no epileptiform activity.
The second twin was seizure-free from 5 to 12 months of age. She experienced febrile seizures at 12 months, and four to five non-febrile, self-limited seizures after 24 months of age, requiring an adjustment of carbamazepine dosage from 10 to 20 mg/kg/day. At 3 years and 4 months of age, she has normal neurodevelopment and a normal neurological examination. EEGs at 5, 9, 16, and 18 months showed no epileptiform activity.
Discussion
These cases illustrate the non-dichotomous clinical variability of KCNQ2-related disorders and the absence of a strict genotype-phenotype correlation. While genotype-phenotype associations have been described – truncating variants and large deletions are more frequently associated with SNE, while de novo missense variants predominate in NEE due to severe functional impairment of potassium currents – the three cases reported demonstrate a continuum of phenotypes.1
The first patient’s clinical course is consistent with classic SNE, presenting early seizure resolution and normal neurodevelopment. In contrast, the twin sisters exhibited a more severe neonatal presentation, both clinically and electrographically, with multifocal epileptiform activity and episodes of status epilepticus. Despite sharing the same genotype, their clinical evolution diverged slightly. One twin developed mild neurodevelopmental delay but achieved sustained seizure freedom, while the other maintained normal development but experienced later seizure recurrence requiring treatment adjustments. Their overall outcomes were more favorable than those typically described in NEE, which supports the existence of intermediate phenotypes between SNE and NEE.1
Factors such as incomplete penetrance and epigenetic mechanisms may contribute to phenotypic variability despite identical genotypes. This is exemplified by the first case, as the same pathogenic variant was identified in an asymptomatic parent, and by the differing epilepsy trajectories observed between monozygotic twins.1
These cases also emphasize the critical role of genetic testing in neonatal epilepsy. In KCNQ2-related disorders, sodium channel-blocking antiseizure medications are often the most effective treatment and may be used as monotherapy.4–6 Specific electroclinical features, such as tonic seizure onset, seizure clustering, and prolonged postictal suppression, are highly suggestive of this genetic etiology and should prompt early consideration of sodium channel blockers.7 Early genetic diagnosis may allow for the timely optimization of therapy, earlier discontinuation of treatment in SNE, and appropriate family counseling regarding recurrence risk in future pregnancies.1
Acknowledgments
The authors acknowledge the collaboration of the Genetics Department of the Hospital de Santa Maria, Unidade Local de Saúde Santa Maria.
Author contributions
I. Brito: conception and design of the study, report, review or other type of work or paper; scquisition of data either from patients, research studies, or literature; analyisis or interpretation of data either from patients, research studies, or literature; drafting the article; final approval of the version to be published; agreement to be accountable for the accuracy or integrity of the work. G. Bonifácio, J.P. Monteiro, and J. Carvalho: conception and design of the study, report, review or other type of work or paper; acquisition of data either from patients, research studies, or literature; analyisis or interpretation of data either from patients, research studies, or literature; critical review of the article for important intellectual content; final approval of the version to be published; agreement to be accountable for the accuracy or integrity of the work.
Funding
None.
Conflicts of interest
None.
Ethical considerations
Protection of human subjects and animals. The authors declare that no experiments on humans or animals were performed for this research.
Confidentiality, informed consent, and ethical approval. The authors have followed their institution’s confidentiality protocols, obtained informed consent from all patients, and secured approval from the Ethics Committee. SAGER guidelines have been followed as applicable to the nature of the study.
Declaration on the use of artificial intelligence. The authors declare that AI was used for the translation task.
