

Keypoints
What is known
– Pityriasis lichenoides chronica is a rare cutaneous inflammatory disease with unknown etiology.
– Pityriasis lichenoides chronica occurs most frequently in children and adolescents, presenting a chronic, fluctuating clinical course with periods of exacerbation and remission.
– The cutaneous lesions are characterized by scaly papules, which may be asymptomatic or cause pruritus, primarily affecting the torso and limbs.
What is added
– The presence of lesions at different stages of development represented a significant clinical finding in raising diagnostic suspicion, reinforcing this clinical criterion as a crucial clue in the initial assessment.
– A complete therapeutic response was observed with regressive topical corticosteroid treatment, demonstrating that less invasive approaches can achieve full lesion resolution while avoiding the potential adverse effects of systemic therapies.
– This case highlights the importance of annual dermatologic follow-up, even in apparently benign forms, due to its potential – albeit rare – risk of malignant transformation.
Introduction
Pityriasis lichenoides encompasses a spectrum of rare inflammatory skin diseases – pityriasis lichenoides chronica (PLC), pityriasis lichenoides et varioliformis acuta (PLEVA), and the febrile ulceronecrotic variant (FUMHD) – which likely represent different manifestations of the same underlying condition.1,2,3 PLC is a rare inflammatory skin disease with uncertain etiology. However, studies suggest it may result from a hypersensitivity reaction to infectious agents, while other theories point to a primary lymphoproliferative disorder.1 Cutaneous lesions are characterized by scaly papules, which can be asymptomatic or cause pruritus, primarily affecting the torso and limbs. The lesions typically present at different stages of development, a fundamental clinical finding to consider in differential diagnosis. Although considered a benign condition, follow-up is recommended due to the rare but possible progression to cutaneous T-cell lymphoma.
Case report
A 15-year-old male adolescent presented to the emergency department with a generalized, recurrent, asymptomatic rash that had been developing over five months. There was no history of fever, recent infections, medication use, or similar cases in family members. Past medical and family history were unremarkable. Dermatological examination revealed oval erythematous scaly papules, some with slight erosion and others purpuric, predominantly distributed over the abdomen and proximal extremities bilaterally, with no involvement of the palms or soles of the feet (Figs. 1 A and B). The lesions were at different stages of development. No lymphadenopathy was detected.
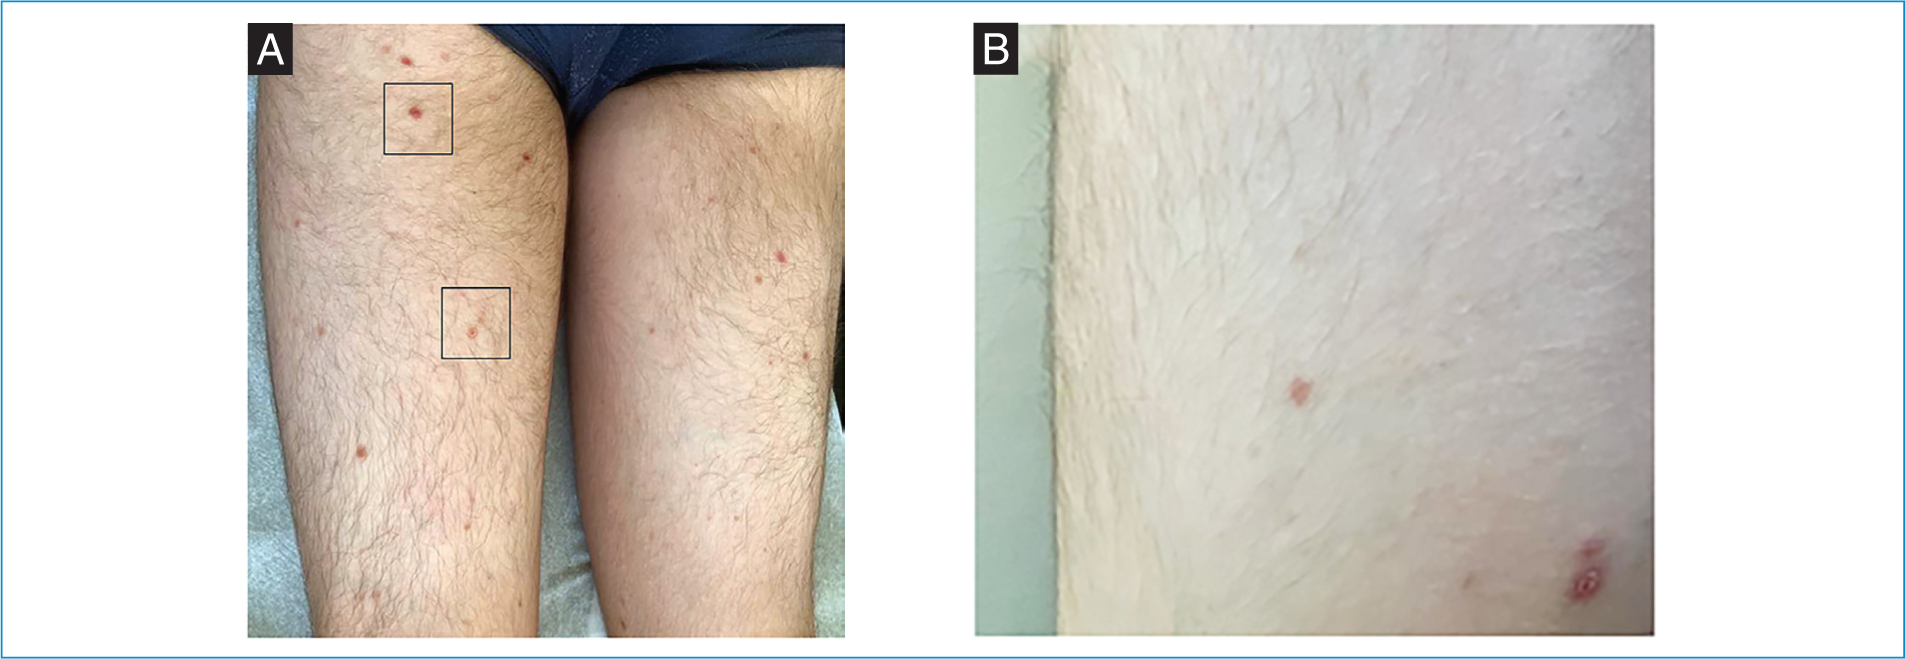
Figure 1. Clinical images. A: clinical image showing oval erythematous-scaly and purpuric papules on the lower limbs. B: erythematous scaly papule on the left upper limb.
A skin biopsy was performed, revealing mild to moderate inflammatory infiltrate in the dermis and hydropic degeneration of the basal layer associated with a moderate lymphocytic infiltrate at the dermoepidermal junction (Fig. 2), and confirming the diagnostic suspicion of PLC. The patient was treated with a potent corticosteroid (clobetasol propionate) daily for two weeks, followed by weekend-only application for an additional four weeks, resulting in significant clinical improvement. During the 12-month follow-up period, no recurrence of the disease was observed.
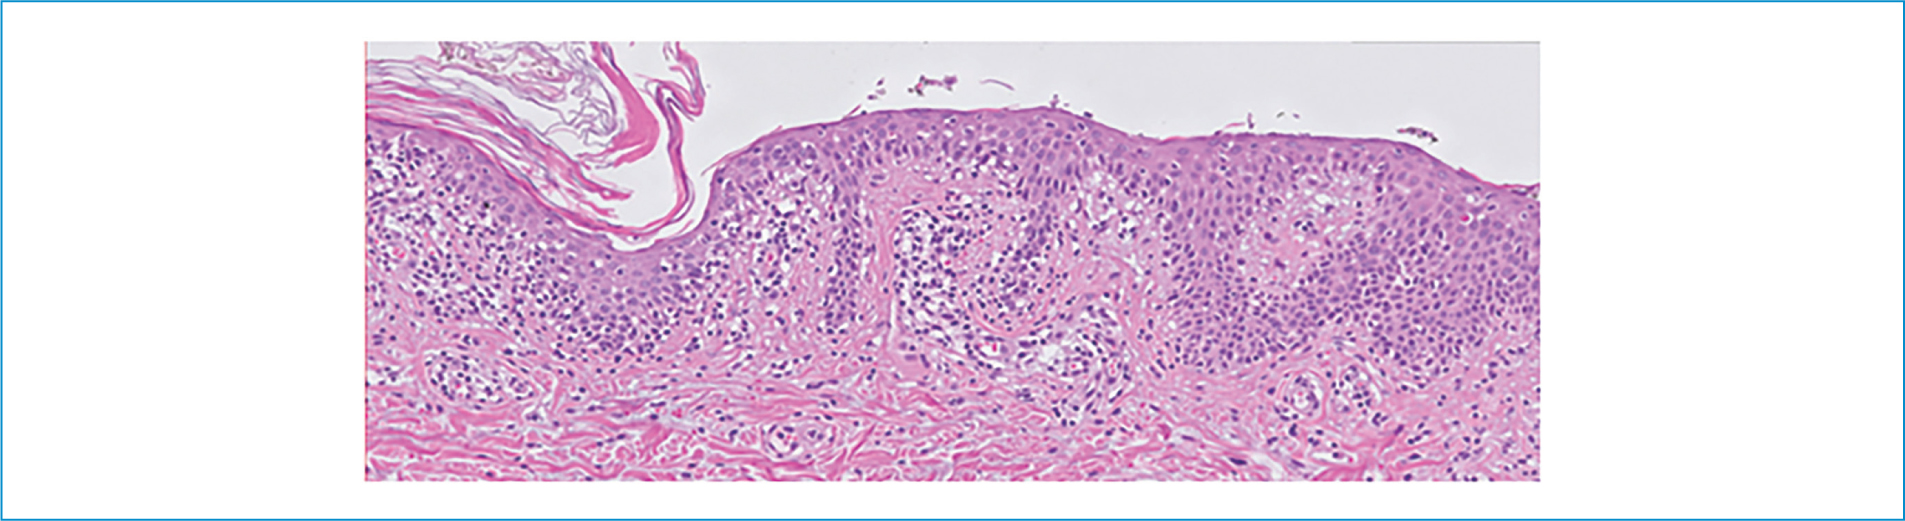
Figure 2. HE 200x biopsy – hydropic degeneration of the basal layer associated with moderate lymphocytic infiltrate at the dermoepidermal junction.
Discussion
This case illustrates an uncommon condition whose non-specific clinical manifestations can make diagnosis challenging. PLC occurs most frequently in children and adolescents, presenting a chronic, fluctuating clinical course with periods of exacerbation and remission.2 Given its non-specific presentation, several differential diagnoses must be considered, including pityriasis rosea, guttate psoriasis, secondary syphilis, lichen planus, and drug eruption.3 As demonstrated in our case, clinical examination combined with histopathology is essential for establishing an accurate diagnosis and distinguishing PLC from these similar conditions.3
Although treatment is not mandatory, it can improve the appearance of skin lesions. In our patient, topical corticosteroids proved to be effective, aligning with current evidence suggesting that topical corticosteroids are particularly beneficial in localized disease. Nevertheless, ultraviolet B (UVB) phototherapy has been demonstrated to be a safe option in this age group,2 thus representing the subsequent therapeutic step should there be no response to topical corticosteroid treatment. Beyond these therapeutic options, and in cases of more extensive disease, oral antibiotics4 or UVB phototherapy, either as monotherapy or in combination with topical corticosteroids, are viable alternatives. Methotrexate is considered a reasonable alternative, particularly for patients with severe forms of the disease.1,5 The clinical course of PLC is characterized by spontaneous remissions and exacerbations, typically resulting in complete resolution, although some cases may persist for years. Our patient demonstrated no recurrences during the 12-month follow-up period, indicating a favorable therapeutic response. Despite its typically benign nature, the rare risk of progression to lymphoproliferative malignancies warrants annual dermatological assessment and vigilance for atypical lesions.6
Author contributions
All authors contributed to the conceptualization, formal analysis, validation and writing (original draft).
Funding
None.
Conflicts of interest
None.
Ethical considerations
Protection of humans and animals. The authors declare that no experiments involving humans or animals were conducted for this research.
Confidentiality, informed consent, and ethical approval. The authors have followed their institution’s confidentiality protocols, obtained informed consent from patients, and received approval from the Ethics Committee. The SAGER guidelines were followed according to the nature of the study.
Declaration on the use of artificial intelligence. The authors declare that no generative artificial intelligence was used in the writing of this manuscript.
